By
For someone who needs an infusion every few weeks, the setting affects more than the appointment itself. It determines how far the person travels, how long the visit takes, who monitors a reaction, and whether the next dose is ready on time.
Providers face a related question: how can they make recurring treatment easier to access without losing the clinical oversight that keeps it safe?
Outpatient infusion services are an increasingly important option for people who need recurring medication without hospital admission.
Biologic therapies, prolonged antibiotics, hydration treatment, and immune-based drugs often require professional observation but not always an overnight stay.
Dedicated centers can provide that oversight in a controlled setting. For suitable patients, this approach may free hospital capacity and give people a more predictable treatment routine while preserving access to hospital care when complications arise.
- TL;DR
- Why Demand Is Rising
- Chronic Conditions Require Ongoing Care
- Hospitals Need Better Resource Allocation
- Patient Comfort Influences Care Choices
- Home-Based Care Adds Flexibility
- Better Coordination Supports Safer Treatment
- Technology Improves Clinical Visibility
- Staffing Must Match Patient Volume
- Financial Factors Shape Expansion
- What Patients Can Expect
- Final Thoughts
- Frequently Asked Questions
TL;DR
- Recurring care is the main driver. Patients receiving biologics, antibiotics, immune therapies, or other infusions may need a series of visits without an overnight hospital stay. A predictable outpatient schedule can make that course easier to manage.
- The setting must fit the treatment. Hospital outpatient departments, ambulatory centers, physician offices, and home care offer different levels of monitoring, access, and support. The patient’s condition and the therapy’s requirements should guide the choice.
- Convenience depends on coordination. A visit can be delayed by missing laboratory results, authorization, medication delivery, or an unclear handoff. Confirming those steps before booking helps protect treatment continuity.
- Capacity is more than chair count. Staffing skills, drug preparation, infusion time, and observation periods determine how many visits a service can handle safely. Providers should study actual scheduling peaks before expanding space or hours.
- Costs need a full-pathway view. Alternative settings can cost less for suitable patients, but savings vary by therapy, payer, and operating model. Drug waste, transport, follow-up, and escalation belong in the calculation.
- Patient experience remains a care measure. Travel, comfort, clear instructions, and access to the clinical team between doses affect how manageable repeated treatment feels. These benefits matter only when safe administration and follow-up remain reliable.
Why Demand Is Rising
Patients on biologic drugs, antibiotics, hydration, or immune therapies often need repeated appointments rather than hospital admission.
For example, Acelpa Health coordinates specialty infusion care, clinical monitoring, and related administrative work across treatment settings. A coordinated arrangement can reduce travel demands for suitable patients, support treatment continuity, and give prescribing clinicians clearer updates about tolerance, symptoms, and progress. The focus remains on safe administration, timely follow-up, and a setting suited to each person’s medical needs.
Interest is visible in provider planning, although no single figure captures all outpatient infusion demand.
In a 2025 survey of nearly 200 cancer-center leaders and staff, 53% said their centers were actively expanding services.
The survey is vendor-sponsored and focused on cancer centers; it is a signal of expansion plans in that group, not a national utilization trend.
CMS reporting on the narrower Medicare home infusion therapy benefit, for example, shows fluctuating service visits from early 2023 through mid-2025 rather than steady growth.
The practical drivers are easier to see at the patient and clinic level: recurring therapies, pressure on hospital capacity, travel burden, and the need to keep medication administration connected to the prescriber’s plan.
Whether those drivers justify a new center, more appointment hours, or a home model depends on the local patient mix and the treatments involved.
Chronic Conditions Require Ongoing Care
Many immune disorders, neurological diseases, and inflammatory conditions involve treatment over several weeks or months. Frequent hospital visits can create transportation problems, missed work, and physical fatigue.
Outpatient appointments offer a consistent schedule, allowing nurses to review symptoms before each dose. Regular observation also helps clinicians recognize changes in blood pressure, allergic response, hydration status, or disease activity. Together, these features can make an ongoing treatment course easier for a patient to manage.
Consistency is an operational task as much as a scheduling preference. A patient who has the next appointment on the calendar may still miss a dose if an authorization expires, a required laboratory result is unavailable, or the drug has not arrived.
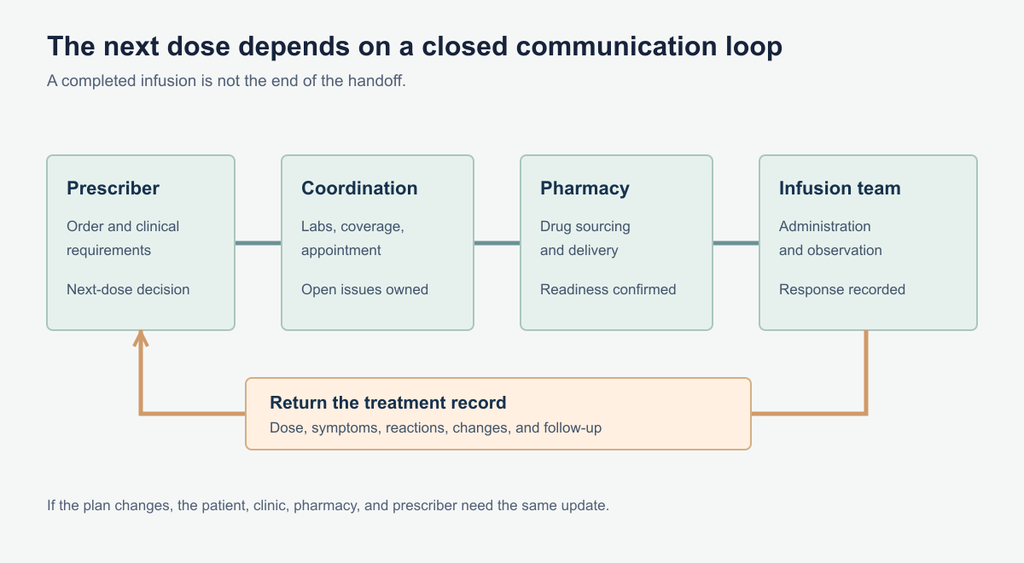
The clinic needs to know which of those steps must be repeated before every visit and which can be confirmed once for the course of therapy. When a dose changes, the prescriber, pharmacy, payer team, and infusion staff should receive the same update.
For patients, continuity also means knowing whom to call between appointments. Side effects or new symptoms may change the plan for the next dose.
A reliable outpatient service gives the prescribing clinician enough information to make that decision and gives the patient a clear route for reporting concerns. The convenience of a regular location is valuable only when that clinical loop stays intact.
Hospitals Need Better Resource Allocation
Hospital beds and nursing teams must remain available for surgery, acute infection, unstable cardiac conditions, and other urgent needs.
Moving suitable infusion treatments to dedicated centers can reduce pressure on inpatient departments. Patients still need clinical supervision, medication verification, and emergency planning.
The difference lies in location: routine therapy need not always occupy resources intended for higher-acuity cases.
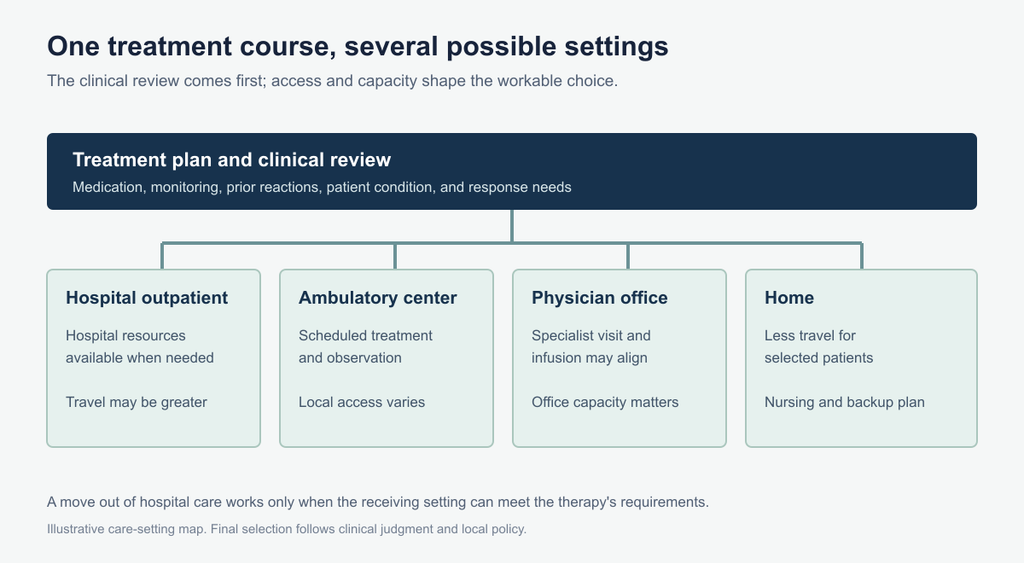
That benefit should be assessed therapy by therapy. Some patients need a hospital outpatient department because of their condition, the medication, or the support available if a reaction occurs.
Others may receive scheduled treatment in an ambulatory center or office with an appropriate monitoring and escalation plan. The aim is to place care where its requirements can be met, rather than shift every infusion into the least expensive setting.
One hospital’s experience illustrates the possible effect on capacity. A quality-improvement study of an integrated outpatient infusion suite reported that the average length of stay for selected elective chemotherapy admissions fell from 105.8 to 95.5 hours after the workflow change.
This was a single-center project tied to a particular regimen, so its result is not a general forecast for other services. It does show that infusion location and timing can affect how long a hospital bed is occupied.
Patient Comfort Influences Care Choices
A quieter clinic may feel less stressful than a busy hospital department. Patients can discuss side effects, medication concerns, and treatment expectations with nursing staff before therapy begins. Comfortable seating, shorter registration processes, and familiar faces may also reduce anxiety. Emotional ease does not replace medical standards, yet it can influence whether a person attends appointments consistently and reports symptoms promptly.
Comfort includes predictability. Patients planning repeated visits need to know how long the infusion and observation are likely to take, whether a companion may attend, and what happens if treatment is delayed. Travel time, parking, accessibility, and a workable return trip can matter as much as the chair itself. Asking about these issues before the first appointment can reveal barriers the clinical order does not show.
Providers should be careful not to equate a more pleasant room with a better treatment plan. A center may offer a calm experience but still cancel visits because medication or authorization is not ready.
Patient experience should be evaluated across the complete course: scheduling, check-in, administration, follow-up, and the ability to reach the team when something changes.
Home-Based Care Adds Flexibility
Certain therapies may be administered at home when the medication, diagnosis, and patient condition meet clinical requirements. A qualified nurse can assess the individual, prepare supplies, administer treatment, and document the response.
Before approval, clinicians should review household safety, refrigeration needs, caregiver availability, and emergency instructions. Home visits can limit travel, especially for patients living far from infusion centers.
Home is one option within outpatient care, not an automatic next step for every stable patient. The team must consider how the medication is delivered and stored, what monitoring is needed during and after administration, whether the patient or caregiver needs training, and how help will arrive if a problem occurs.
Patient preference matters too; some people value the convenience of home, while others feel more comfortable in a staffed center.
Coverage needs its own check. CMS defines the Medicare home infusion therapy benefit for certain drugs and biologicals administered through a qualifying pump, along with specified professional services.
That benefit is narrower than the everyday phrase “home infusion.” Providers should verify the specific drug, benefit, payer, and nursing arrangement before promising a home option to a patient.
Better Coordination Supports Safer Treatment
Infusion therapy involves prescribers, pharmacists, nurses, insurers, manufacturers, and patients. Missing laboratory results or incomplete authorization details can postpone a scheduled dose.
Care coordinators help verify orders, track approvals, arrange medication delivery, and confirm appointments. Accurate communication also allows the prescribing team to respond quickly when a patient reports fever, rash, breathing difficulty, or another possible reaction.
The fragile point is often the handoff before the first visit. A referral can be accepted while the order lacks a needed detail, the authorization covers a different setting, or the pharmacy has no confirmed delivery date. A shared readiness status should tell the scheduler whether the visit is clinically reviewed, financially cleared, and supplied. If a step remains open, someone needs to own it and tell the patient when to expect an update.
A 2025 study of two hospital-based infusion clinics found that after financial-clearance work was centralized, denials related to that workflow fell by 68%, with approximately $1.4 million less in associated denied amounts.
This is one health system’s quality-improvement finding, not a savings target for other providers. Its relevance is the process: authorization and benefit checks are part of treatment readiness, not paperwork to resolve after a patient has been booked.
Technology Improves Clinical Visibility
Electronic medical records give authorized staff access to medication history, allergies, laboratory findings, and previous reactions. Standardized notes reduce confusion between a physician’s office and an infusion center.
Secure messaging can deliver updates without relying on disconnected paperwork. Remote follow-up may identify delayed reactions after treatment. Technology remains a support tool, while clinical judgment determines whether therapy should continue.
The most useful technology makes the next action visible. A scheduler should be able to see that the drug is delayed without viewing every pharmacy detail.
A nurse should know that a new symptom has been reviewed by the prescriber. The prescriber should receive a clear account of a missed or modified dose. Those signals can come from several systems, but their status and owner should agree.
Before adding another dashboard, leaders should define the questions it must answer: Which visits are at risk this week? Why were doses postponed? How long did patients wait between referral and first treatment? Which reactions required escalation? If the system cannot answer those questions without a manual search across messages and notes, the coordination problem remains.
Staffing Must Match Patient Volume
Rising demand requires sufficient nurses, pharmacists, technicians, and administrative personnel.
Clinical staff need training in medication preparation, infection control, adverse reaction management, and patient education. Appointment volume should also account for observation periods and unexpected treatment delays.
Adequate coverage protects safety, limits fatigue, and gives each patient enough time to receive careful assessment before leaving the facility.
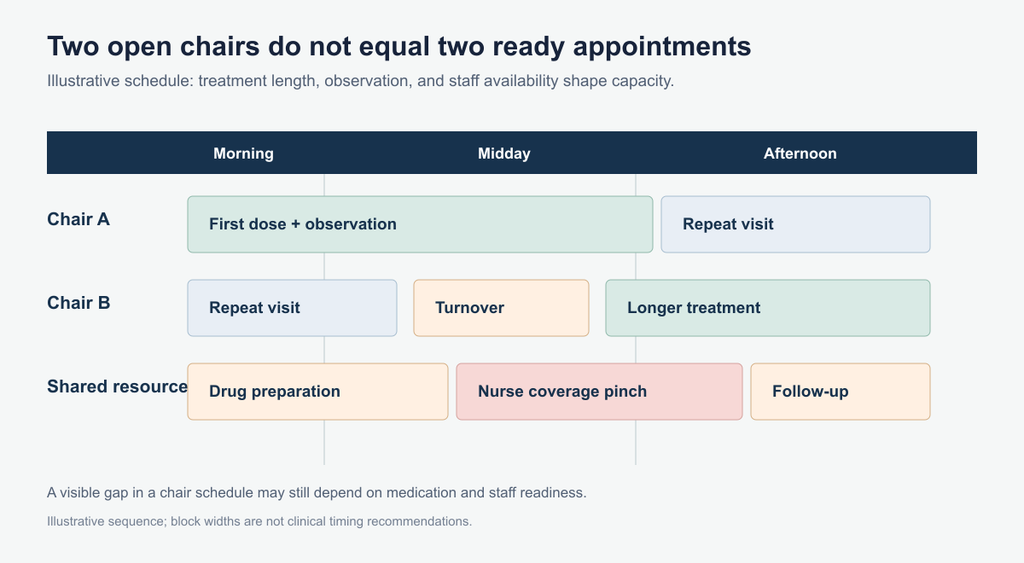
Chair count alone is a poor measure of capacity. A first dose may require a longer visit than a repeat dose; some therapies need specific competencies or more pharmacy preparation time.
An infusion that begins late can occupy a chair into the next patient’s slot. Providers should review actual start and finish times by therapy, alongside nurse availability and medication release times, before concluding that they need more physical space.
In the 2025 cancer-center survey, 62% of respondents named patient flow and scheduling as their leading operational challenge, and 47% cited midday peaks.
Those figures describe the surveyed cancer centers, not every infusion practice. They point to a useful local test: map where the day bunches up, then decide whether the answer is a different schedule, pharmacy cutoff, skill mix, or additional capacity.
Financial Factors Shape Expansion
Health plans review whether a therapy occurs in a suitable setting. Outpatient delivery may reduce facility charges when admission is unnecessary, although total costs include medication, staffing, transportation, monitoring, and follow-up.
Providers should assess the full treatment pathway rather than just one invoice. Reliable records help insurers and care teams compare spending with treatment continuity, symptom control, emergency visits, and patient outcomes.
A 2026 matched claims study of 52,760 infusions among 18,988 commercially insured patients found that outpatient costs were 41.9% higher after infusions in hospital outpatient departments than after infusions in alternative settings.
In the matched sample, the researchers did not find a significant difference in serious or mild adverse events over the short follow-up period. They excluded cases where a hospital outpatient department was medically necessary.
The study supports evaluating site-of-care costs; it does not establish that every patient can change setting or that a new center will save the same amount.
For a provider considering expansion, the relevant calculation uses local therapy mix and payer contracts. It should include drug acquisition and waste, staffing, preparation time, authorization work, cancellations, and the cost of handling complications or transfers.
The financial question is strongest when paired with an access question: will the proposed setting make a recurring course easier for the patients who need it, without shifting unmanageable work to another team or to the patient?
What Patients Can Expect
A typical visit begins with registration, medication reconciliation, and a brief health assessment. Nurses may check vital signs, review recent symptoms, and confirm allergies before starting treatment. Infusion time depends on the drug, dose, and individual response. Staff may continue observation afterward, and they usually inform patients about warning signs, fluid intake, follow-up scheduling, and after-hours contact procedures.
The exact sequence varies by therapy and setting. Before the first visit, the patient should know the expected duration, what information or test results the team needs, whether transportation or a companion is required, and whom to contact if their health changes. During the visit, staff can explain what they are checking and how the next dose will be arranged. Afterward, a clear written or approved digital follow-up message helps the patient and prescriber stay aligned.
That practical clarity matters to the provider too. When patients know what to expect, staff spend less time resolving avoidable day-of-service surprises. A missed appointment or late cancellation should still be reviewed for its actual cause, which may be transport, an authorization gap, a medication delay, or a change in clinical condition rather than a lack of patient commitment.
Final Thoughts
Outpatient infusion services address several issues in modern care delivery, including recurring treatment needs, limited hospital capacity, and transportation barriers.
Dedicated centers can provide medication administration, observation, education, and follow-up without requiring an overnight admission. Home care adds another option for selected patients.
As more organizations evaluate where to deliver scheduled therapies, the strongest programs will keep the treatment plan, clinical monitoring, medication supply, and patient experience connected from one dose to the next.
Frequently Asked Questions
Why are outpatient infusion services in demand?
Many therapies require repeated administration and observation without an overnight admission. Patients may value predictable visits closer to home, while providers seek to use hospital resources for care that needs them. Demand varies by therapy and local market.
Is an ambulatory infusion center suitable for every patient?
No. The prescriber and infusion team must consider the patient’s condition, the medication, monitoring requirements, previous reactions, and the site’s ability to respond to complications. Some patients need hospital-based care.
How is home infusion different from treatment at an infusion center?
Home infusion brings an eligible therapy and appropriate nursing support to the patient. A center provides a staffed treatment space with on-site monitoring and shared resources. The right choice depends on clinical suitability, home circumstances, patient preference, and coverage.